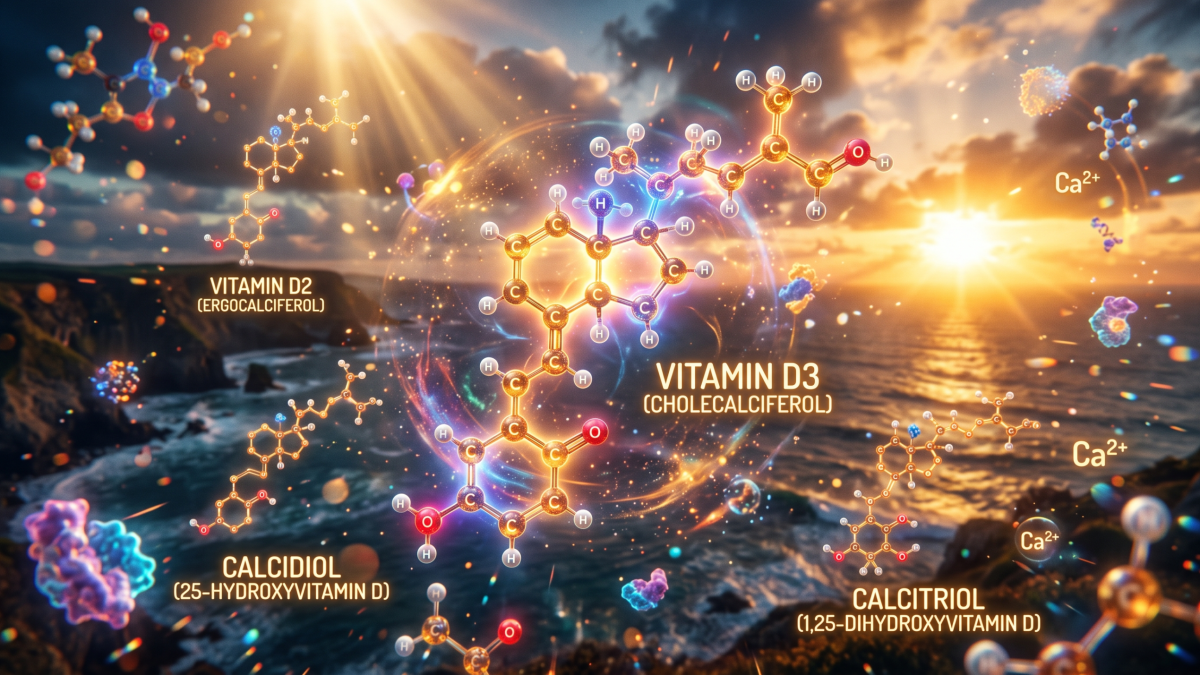
Introduction: Why Vitamin D is a Hormone, Not a Simple Nutrient
For women over 45, the transition into perimenopause and menopause represents one of the most profound physiological shifts of their lives. While much of the public discussion surrounds estrogen and progesterone, there is a silent, often overlooked regulator that dictates how smoothly this transition occurs: Vitamin D.
Despite its historical classification, modern biochemistry recognizes Vitamin D not as a simple dietary nutrient, but as a potent secosteroid hormone. Receptors for Vitamin D (VDR) are expressed in almost every tissue in the human body, from skeletal muscle and osteoblasts to immune cells and the brain.
During menopause, the steep decline in ovarian hormones specifically estradiol disrupts systemic homeostasis, triggering hot flashes, bone loss, sleep disturbances, and altered immune responses. Ensuring optimal Vitamin D levels during this critical period is not merely a recommendation; it is an absolute biochemical necessity to protect your bones, modulate your immune system, and support long-term metabolic health.
The Menopause Transition: Estradiol, Cortisol, and Metabolic Shift

During the climacteric years, the ovaries gradually deplete their follicular reserve, leading to a dramatic drop in estradiol levels. This estrogen deficiency causes a cascade of metabolic adaptations:
- Hormonal Imbalance and Cortisol Spikes: As estrogen and progesterone levels fall, the adrenal glands often compensate, leading to relative cortisol dominance. Elevated cortisol (the stress hormone) directly opposes the action of progesterone, accelerates bone resorption, impairs sleep quality, and promotes visceral fat accumulation.
- Insulin Resistance and Visceral Fat: The shift in the estrogen-to-androgen ratio alters fat distribution, favoring the accumulation of visceral “menopause belly” fat. This tissue is highly active metabolically, secreting pro-inflammatory cytokines that drive systemic insulin resistance and elevate cardiovascular risk.
- Low-Grade Systemic Inflammation: This chronic, subclinical inflammatory state often referred to as “inflammaging” is exacerbated by the loss of estrogen’s natural anti-inflammatory actions, making the body more vulnerable to joint pain, metabolic dysfunction, and immune senescence.
Vitamin D acts as a critical counter-regulatory hormone in this environment, modulating genomic transcription to suppress pro-inflammatory pathways and support metabolic signaling.
Section 1: Bone Density and Osteoporosis Prevention
The primary and most widely recognized role of Vitamin D is the maintenance of skeletal integrity. However, the mechanisms behind this during menopause are deeply intertwined with the hormonal environment.
The Estrogen-Calcium-Vitamin D Triad
Estrogen plays a key role in protecting bones by inhibiting the activity of osteoclasts (the cells responsible for bone breakdown). When estradiol levels plummet during menopause:
- Osteoclast activity is unchecked, leading to rapid bone resorption.
- Intestinal calcium absorption drops significantly, independent of dietary intake.
- Renal calcium retention is compromised.
To absorb calcium from the gastrointestinal tract, the body requires active 1,25-dihydroxyvitamin D (calcitriol). Without adequate Vitamin D, the body can only absorb about 10% to 15% of dietary calcium. When blood calcium levels fall, the parathyroid glands release parathyroid hormone (PTH), which triggers the extraction of calcium directly from the bones, accelerating osteopenia and osteoporosis.
Clinical Evidence & Rigor
Numerous clinical trials published in databases like PubMed demonstrate that Vitamin D supplementation, especially when combined with calcium, significantly reduces bone mineral density (BMD) loss and decreases fracture risk in postmenopausal women. A landmark study published in The New England Journal of Medicine confirmed that optimal postmenopausal bone preservation requires maintaining serum 25-hydroxyvitamin D levels above 30 ng/mL, showing a dramatic reduction in non-vertebral fractures when compared to deficient control cohorts.
Section 2: The Immune Shield — Vitamin D as an Immunomodulator
Beyond its skeletal benefits, Vitamin D is a primary driver of immunomodulation. During menopause, women experience a natural decline in immune function (immune senescence), leaving them more susceptible to viral infections, urinary tract infections (UTIs), and chronic inflammatory conditions.
                  [ Active Vitamin D (Calcitriol) ]
                                 │
         ┌───────────────────────┴───────────────────────┐
         ▼                                               ▼
[ Innate Immunity ]                             [ Adaptive Immunity ]
  • Stimulates Cathelicidin                       • Suppresses Th1/Th17 cells
    and Defensins (Antimicrobials)                  (Reduces Autoimmunity)
  • Enhances Macrophage phagocytosis              • Promotes Treg cell activity
  • Direct defense against pathogens                (Anti-inflammatory signal)
Strengthening Innate and Adaptive Immunity
Vitamin D receptors are highly concentrated on macrophages, dendritic cells, and T- and B-lymphocytes. Active Vitamin D regulates the immune response in two main ways:
- Enhancing Innate Defense: Vitamin D stimulates the transcription of antimicrobial peptides, such as cathelicidin and defensins, which act as the body’s natural antibiotics, directly destroying the cell walls of invading bacteria and viruses.
- Suppressing Adaptive Hyper-reactivity: Vitamin D suppresses the overactivation of helper T-cells (specifically Th1 and Th17 pathways), which produce inflammatory cytokines. Instead, it promotes the differentiation of regulatory T-cells (Tregs), which act as “brakes” on the immune system, preventing autoimmune flares and chronic low-grade inflammation.
By maintaining optimal Vitamin D levels, menopausal women can significantly lower their risk of chronic inflammatory joint pain, recurrent UTIs, and respiratory infections, providing a robust, natural shield for their daily well-being.
Section 3: Combating Sarcopenia and Joint Pain
As women age, they face a progressive loss of skeletal muscle mass, strength, and function a clinical condition known as sarcopenia. Estrogen decline plays a direct role in muscle degeneration, but Vitamin D deficiency acts as an accelerant.
The Role of VDR in Muscle Tissue
Skeletal muscle cells express specific Vitamin D receptors (VDR). The binding of active Vitamin D to these receptors promotes protein synthesis, muscle cell proliferation, and the growth of Type II (fast-twitch) muscle fibers, which are the first to atrophy during aging. Supplementation has been shown to:
- Improve lower-limb muscle strength and postural balance.
- Significantly reduce the incidence of accidental falls in older adults.
- Alleviate chronic muscle pain and stiffness associated with the menopause transition.
Furthermore, Vitamin D modulates joint health by reducing the production of inflammatory prostaglandins and metalloproteinases in joint cartilage, helping to ease the joint stiffness and muscular discomfort that frequently manifest in women over 45.
Section 4: Optimal Dosage, Testing, and Safety

Achieving the therapeutic benefits of Vitamin D requires a personalized, evidence-based approach rather than guesswork.
Testing and Serum Levels
The only accurate way to evaluate your status is through a 25-hydroxyvitamin D [25(OH)D] blood test.
- Deficiency: Below 20 ng/mL (associated with rapid bone loss and impaired immunity).
- Insufficiency: 20 to 29 ng/mL (suboptimal for metabolic and immune health).
- Optimal Range: 30 to 50 ng/mL (the target zone for therapeutic bone and immune protection).
- Toxicity Risk: Generally occurs only when levels exceed 150 ng/mL, typically driven by massive, unmonitored supplemental doses.
Dosage Recommendations
For most menopausal women, a daily maintenance dose of 1,000 to 2,000 IU of Vitamin D3 (Cholecalciferol) is sufficient to maintain optimal levels. However, if a deficiency is detected, a clinical correction protocol (such as 5,000 IU daily for 8 to 12 weeks) under professional supervision may be required.
The Crucial Synergies: Vitamin K2 and Magnesium
To ensure Vitamin D works safely and effectively, it must be paired with its natural biochemical partners:
- Vitamin K2 (as MK-7): While Vitamin D increases calcium absorption in the gut, Vitamin K2 activates osteocalcin and Matrix Gla Protein (MGP), which act as traffic directors, routing calcium directly into the bone matrix and preventing it from depositing in the arteries or kidneys (vascular calcification).
- Magnesium: The enzymes that convert Vitamin D into its active form in the liver and kidneys are completely magnesium-dependent. Deficient magnesium levels can render supplemental Vitamin D biologically inactive.
Pharmacist’s Editorial Note and E-E-A-T Disclaimer
With over 20 years of clinical experience as a practicing pharmacist specializing in Homeopathy and Phytotherapy (CRF 9930-RJ), my mission is to bridge the gap between rigorous, evidence-based science and natural wellness. The physiological transitions of menopause require a highly individualized approach. While natural therapies offer powerful, restorative benefits, they must be tailored to your unique biochemistry, medical history, and lifestyle.
Medical Disclaimer: The information provided in this article is for educational and informational purposes only and does not constitute medical advice. Always consult your ginecologista, endocrinologista, or trusted health professional before starting any new supplementation protocol, especially if you have underlying health conditions or are taking prescription medications.
Frequently Asked Questions (FAQ)
1. Why is Vitamin D considered more of a hormone than a vitamin?
Vitamin D is classified as a secosteroid hormone because its chemical structure is similar to steroid hormones and it is synthesized endogenously from cholesterol. Unlike classic vitamins, it acts on distant target tissues through specific nuclear receptors (VDR), regulating the transcription of hundreds of genes controlling bone density, metabolism, and immune defenses.2. Can Vitamin D help reduce the “menopause belly” and visceral fat?
Yes, indirectly. Vitamin D deficiency is closely linked to insulin resistance and visceral fat accumulation. By optimizing Vitamin D levels, you support insulin sensitivity and help regulate adipocyte inflammation. When paired with a balanced diet, this helps mitigate the hormonal shift toward abdominal fat storage during menopause.3. How does Vitamin D improve my immune system during menopause?
Vitamin D stimulates the production of antimicrobial proteins like cathelicidin and defensins in immune cells, creating a strong barrier against pathogens. Simultaneously, it modulates adaptive immunity by suppressing pro-inflammatory Th1/Th17 cytokines and boosting regulatory T-cells, which helps control chronic low-grade inflammation and autoimmune reactions.4. Why should I always take Vitamin D3 with Vitamin K2 (MK-7)?
Vitamin D increases intestinal calcium absorption, which raises circulating calcium levels. Without Vitamin K2, this calcium can deposit in your arteries and soft tissues, raising cardiovascular risk. Vitamin K2 activates proteins that direct calcium straight into your bones and teeth, ensuring vascular safety and structural bone support.5. What are the signs that my Vitamin D levels might be too low?
Common signs of postmenopausal Vitamin D deficiency include persistent joint and muscle pain, fatigue, frequent infections, mood fluctuations, and unexplained bone loss. Because these symptoms often overlap with general menopause symptoms, a 25-hydroxyvitamin D blood test is the only reliable way to confirm a deficiency.Vitamin D Menopause: The Science-Backed Guide to Health & Immunity
- Accelerated bone resorption (leading to osteopenia and osteoporosis).
- A rise in systemic low-grade inflammation (often linked to weight gain, joint pain, and “menopause belly”).
- An aging immune response (immunosenescence), leaving the body more vulnerable to infections.
- Successfully increased circulating 25-hydroxyvitamin D [25(OH)D] levels by 45.4%.
- Induced a significant 21.3% decrease in parathyroid hormone (PTH) levels, effectively suppressing excessive bone resorption and stabilizing bone turnover markers.
- IL-5 & IL-12 p70 (linked to inflammatory pathways)
- IL-17A (a major driver of autoimmune activity)
- TNF-alpha & IFN-gamma (primary markers of systemic, age-related inflammation)
- Impaired Insulin Sensitivity: Vitamin D receptors on pancreatic beta-cells help regulate insulin secretion, which is vital for preventing metabolic syndrome.
- Elevated Cortisol Levels: Chronic stress and sleep disturbances during menopause elevate cortisol, which breaks down muscle tissue and promotes abdominal fat storage.
- Muscle Weakness: Vitamin D directly stimulates protein synthesis in muscle fibers, preserving strength, reducing body sway, and decreasing the risk of accidental falls.
- Vitamins D3 and K2 Co-Treatment: While Vitamin D3 increases calcium absorption in your gut, Vitamin K2 (specifically MK-7) acts as the “GPS” that directs that calcium away from your arteries and joints, delivering it straight to your bones.
- Anti-Inflammatory Phytotherapy: Incorporating standardized plant extracts like Ashwagandha (to lower stress-induced cortisol) and Red Clover (rich in phytoestrogens) works beautifully alongside Vitamin D to stabilize hormone fluctuations and support metabolic health.
- Active Lifestyles: Combine your supplementation with resistance exercises. Weight-bearing movements stimulate bone osteoblasts to lay down new bone tissue, working in perfect harmony with Vitamin D.